Skip to content
Epomedicine

Mnemonics, Simplified Concepts & Thoughts

Epomedicine

Mnemonics, Simplified Concepts & Thoughts

Spondylolisthesis : Summary

Epomedicine, Aug 31, 2024Aug 31, 2024

Indications for surgery

Age groupSpondylolisthesisIndications
PediatricLow gradeFailure to respond to conservative treatment (9-12 months)
Progressive slippage
Intractable low back or radicular pain
Neurological deficit and deterioration
High gradeNeurological symptoms
Severe sagittal plane spinal deformity
AdultLow gradeFailure of non-operative treatment
Progressive slippage
Symptomatic and radiographically unstable isthmic spondylolisthesis
High gradeDisabling back and/or low back pain
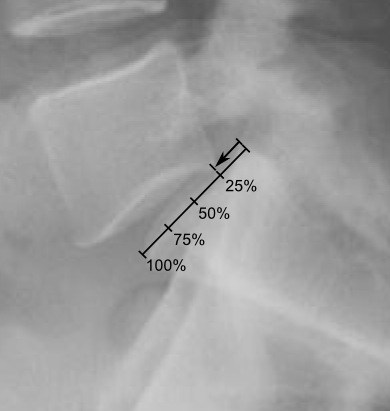
Spondylolisthesis
“Spondylolisthesis measurement on X-ray” by Source image: Chester J Donnally III Annotated by Mikael Häggström, M.D. Author info – Reusing images- Conflicts of interest: None Mikael Häggström, M.D. is licensed under CC BY 4.0.

SDSG classification

Mnemonic: SDSG
1. SDSG classification
2. Degree of slip
3. Spinopelvic balance
4. Global spinal balance

Degree of slipSpinopelvic balanceGlobal spinal balanceTypeRemarksSurgery
Low grade (Meyerding I and II)PI <45 (low PI)C7 plumb line falls over or behind femoral head (Balanced)1Nutcracker – clamping of posterior element of L5 between pars interarticularis of L4 and S1 during extensionInstrumentation and fusion
Postural reduction
PI 45-65 (normal PI)2
PI >65 (high PI)3Shear type –
High grade (Meyerding III, IV, V)SS > PT (Balanced)4
PT > SS (Unbalanced), i.e., retroverted pelvis5Reduction and realignment should be considered
PT > SS (Unbalanced), i.e., retroverted pelvisC7 plumb line falls anterior to femoral head (Unbalanced), i.e., stooping6Reduction and realignment are mandatory

Degenerative spondylolisthesis Instability Classification

ParameterType I, StableType II, Potentially unstableType III, Unstable
LBPNone or very mildPrimary or secondary symptomPrimary or secondary symptom
Restabilization signPresent
Grossly narrowed disc height
Some
Reduced disc height
None
Normal to slightly reduced disc height
Disc angleLordotic disc angles on flexion radiographs or <3 mm translation on dynamic filmsNeutral disc angle on flexion radiographs or 3-5 mm of translation on dynamic filmsKyphotic disc angle on flexion radiographs or >5 mm translation on dynamic films
Joint effusionNo facet joint effusion on MRIFacet joint effusion on MRI without distractionLarge facet joint effusion on MRI
SurgeryDecompression aloneDecompression and posterior fusionDecompression and posterior fusion and interbody fusion

General alignment targets

  • PI – LL < 10°
  • PT < 25°
  • SVA < 5 cm
1 shares
  • Facebook
  • Twitter
PGMEE, MRCS, USMLE, MBBS, MD/MS Musculoskeletal systemOrthopedics

Post navigation

Previous post
Next post

Related Posts

PGMEE, MRCS, USMLE, MBBS, MD/MS gastric glands

Gastric glands and cells

Jul 15, 2018Jun 16, 2023

Anatomically, stomach can be divided into 3 parts from above to below: Gastric pits deepen as we move below from cardiac to pyloric glands. Mucus secreting cells: Present in all 3 glands – cardiac, fundic and pyloric but predominate in cardiac and pyloric glands. Pyloric glands have 1 more cell…

Read More
PGMEE, MRCS, USMLE, MBBS, MD/MS

Elbow Anastomoses : Mnemonic

Mar 14, 2021Mar 14, 2021

First things first. It is essential to understand the meaning of collateral and recurrent arteries. Recurrent arteries turn back so as to reverse direction. Collateral arteries refer to side branches of the major arteries. Mnemonic: M.R. Deep On the posterior aspect of the shaft of the humerus: Profunda brachii (Deep…

Read More
PGMEE, MRCS, USMLE, MBBS, MD/MS choosing hypoglycemics

Approach to Uncomplicated Diabetes Mellitus : Simplified

Feb 19, 2016Jun 12, 2016

A) GLUCOSE LEVEL 1. Post-prandial: 140-200 mg/dl: Impaired glucose tolerance (Pre-diabetes) Diabetes prevented with: weight loss, exercise, metformin (in high risk) ≥200 mg/dl (+ Clinical symptoms): Diabetes confirmed 2. Fasting: 100-126 mg/dl: Impaired fasting glucose (Pre-diabetes) ≥126 mg/dl (+ Clinical symptoms): Diabetes confirmed

Read More

Leave a Reply Cancel reply

Your email address will not be published. Required fields are marked *

This site uses Akismet to reduce spam. Learn how your comment data is processed.

Epomedicine. Spondylolisthesis : Summary [Internet]. Epomedicine; 2024 Aug 31 [cited 2026 Sep 26]. Available from: https://epomedicine.com/medical-students/spondylolisthesis-summary/.

Pre-clinical (Basic Sciences)

Anatomy

Biochemistry

Community medicine (PSM)

Embryology

Microbiology

Pathology

Pharmacology

Physiology

Clinical Sciences

Anesthesia

Dermatology

Emergency medicine

Forensic

Internal medicine

Gynecology & Obstetrics

Oncology

Ophthalmology

Orthopedics

Otorhinolaryngology (ENT)

Pediatrics

Psychiatry

Radiology

Surgery

RSS feed: Ask Epomedicine Ask Epomedicine

  • What to study for Clinical examination in Orthopedics?
  • What is the mechanism of AVNRT?

Epomedicine weekly

  • About Epomedicine
  • Contact Us
  • Author Guidelines
  • Submit Article
  • Editorial Board
  • USMLE
  • MRCS
  • Thesis
©2026 Epomedicine | WordPress Theme by SuperbThemes