Skip to content
Epomedicine

Mnemonics, Simplified Concepts & Thoughts

Epomedicine

Mnemonics, Simplified Concepts & Thoughts

Open Pelvic fractures – Classification

Epomedicine, May 23, 2020May 23, 2020

General principles and classification of open fractures have been discussed earlier. The Gustillo-Anderson classification commonly used for the long bone fractures might not be suitable for open pelvic fractures.

Open fractures : Mnemonics

Jones-Powell classification

It is based on the mechanical stability of the pelvic ring and the potential contamination of the open wound.

Class 1 – Stable pelvic ring

Class 2 – Pelvic ring unstable (no rectal or perineal wound)

Class 3 – Pelvic ring unstable (rectal or perineal wound)

Mortality:

Class 1 – 0%
Class 2 – 24%
Class 3 – 38%

Faringer Classification

It correlates the site of the open wound and the need for colostomy.
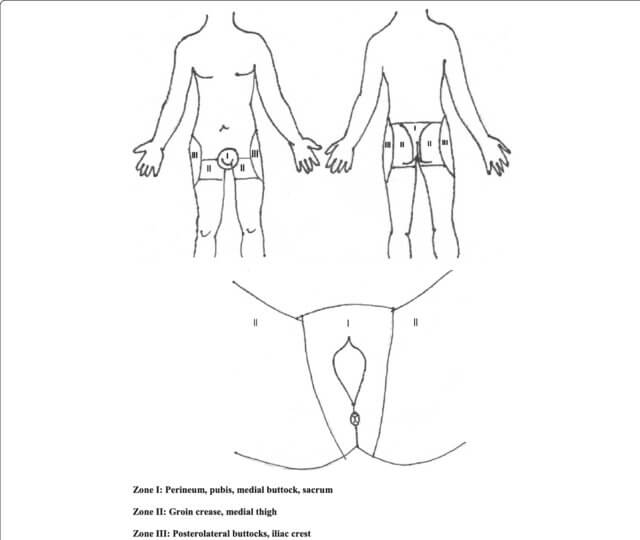
faringer classification
Hermans, E., Edwards, M.J.R., Goslings, J.C. et al. Open pelvic fracture: the killing fracture?. J Orthop Surg Res 13, 83 (2018). https://doi.org/10.1186/s13018-018-0793-2

Zone I: perineum, anterior pubis, medial buttock, posterior sacrum)

Zone II: medial thigh, groin crease

Zone III: posterolateral buttock, iliac crest

Faringer et.al proposed that:

1. Most patients with zone I injuries should undergo fecal diversion.

2. Patients with deep lacerations over the posterior buttock should also be considered candidates for diversion, particularly when prolonged bed rest or fecal incontinence is anticipated.

3. Patients with zone II wounds into the subcutaneous fat located in the anterior groin crease or the medial thigh may selectively require fecal diversion.

4. Fecal diversion is rarely required for wounds in zone III.

References:

1. Cannada LK, Taylor RM, Reddix R, et al. The Jones-Powell Classification of open pelvic fractures: a multicenter study evaluating mortality rates. J Trauma Acute Care Surg. 2013;74(3):901‐906. doi:10.1097/TA.0b013e3182827496

2. Faringer PD, Mullins RJ, Feliciano PD, et al. Selective fecal diversion in complex open pelvic fractures from blunt trauma. Arch Surg. 1994;129:958–64.

  • Facebook
  • Twitter
Emergency Medicine General SurgeryMusculoskeletal systemOrthopedics

Post navigation

Previous post
Next post

Related Posts

Emergency Medicine san francisco syncope rule

San Francisco Syncope Rule (FED 30 90)

Oct 28, 2017Oct 28, 2017

San Francisco Syncope Rule (SFSR) defines high risk criteria for patients with syncope. FED 30 90 Failure (Congestive heart failure) ECG abnormalities Dyspnea (shortness of breath) Hematocrit <30% Systolic blood pressure <90 mmHg (at any time) Presence of any of the above criteria is regarded as positive. Mnemonic: CHESS Congestive…

Read More
Emergency Medicine

Polytrauma Assessment and Management (ATLS) : Mnemonics

Jul 31, 2020Aug 26, 2023

SIEVE triage system Mnemonic: ABC-30-2 Can Do Approach to assessment and initial management Mnemonic: ARM Adjuncts to Primary Survey Reflects the adequacy of resuscitation. Mnemonic: PEA COVER Primary Survey Follow the look, listen, feel approach – Mnemonic: ABCDE 1. Airway and C-spine protection: 2. Breathing: 3. Circulation and control of…

Read More
Emergency Medicine

Circumferential Periosteal Block (CPB)

May 28, 2023May 28, 2023

Use: Alternative to hematoma block in reduction of distal radius and ulna fractures Advantage: Providing distance from the fracture hematoma (no theoretical risk of converting closed fracture into open fracture) Disadvantage: Risk of neurovascular injury on volar surface of forearm Local anesthetic and volume: 10–15 ml of 1 % plain lidocaine…

Read More

Leave a Reply Cancel reply

Your email address will not be published. Required fields are marked *

This site uses Akismet to reduce spam. Learn how your comment data is processed.

Epomedicine. Open Pelvic fractures – Classification [Internet]. Epomedicine; 2020 May 23 [cited 2026 Sep 26]. Available from: https://epomedicine.com/emergency-medicine/open-pelvic-fractures-classification/.

Pre-clinical (Basic Sciences)

Anatomy

Biochemistry

Community medicine (PSM)

Embryology

Microbiology

Pathology

Pharmacology

Physiology

Clinical Sciences

Anesthesia

Dermatology

Emergency medicine

Forensic

Internal medicine

Gynecology & Obstetrics

Oncology

Ophthalmology

Orthopedics

Otorhinolaryngology (ENT)

Pediatrics

Psychiatry

Radiology

Surgery

RSS feed: Ask Epomedicine Ask Epomedicine

  • What to study for Clinical examination in Orthopedics?
  • What is the mechanism of AVNRT?

Epomedicine weekly

  • About Epomedicine
  • Contact Us
  • Author Guidelines
  • Submit Article
  • Editorial Board
  • USMLE
  • MRCS
  • Thesis
©2026 Epomedicine | WordPress Theme by SuperbThemes