Skip to content
Epomedicine

Mnemonics, Simplified Concepts & Thoughts

Epomedicine

Mnemonics, Simplified Concepts & Thoughts

Child Pugh Score

Hepatorenal syndrome (HRS) – Quick revision

Epomedicine, Apr 18, 2017

New Criteria for HRS

1. Cirrhosis with ascites

2. Serum creatinine >1.5mg/dl

3. No sustained improvement in renal function after 2 days of diuretic withdrawl (if on diuretics) and volume expansion with albumin infusion at 1 gm/kg/day upto a maximum of 100 gm/day.

4. No evidence of shock

5. No nephrotoxic drugs

6. No evidence of parenchymal kidney disease

  • Proteinuria <0.5 gm/day
  • No microhematuria (RBC <50/hpf)
  • Normal renal ultrasonography

Types of HRS

Type 1 HRS

  • Rapid and progressive impairment in renal function (increase in serum creatinine of ≥100% compared to baseline to a level higher than 2.5mg/dl in <2 weeks)

Type 2 HRS

  • Stable or less progressive impairment in renal function
  • Type 2 HRS may convert to Type 1 HRS spontaenously or following precipitating event such as SBP.
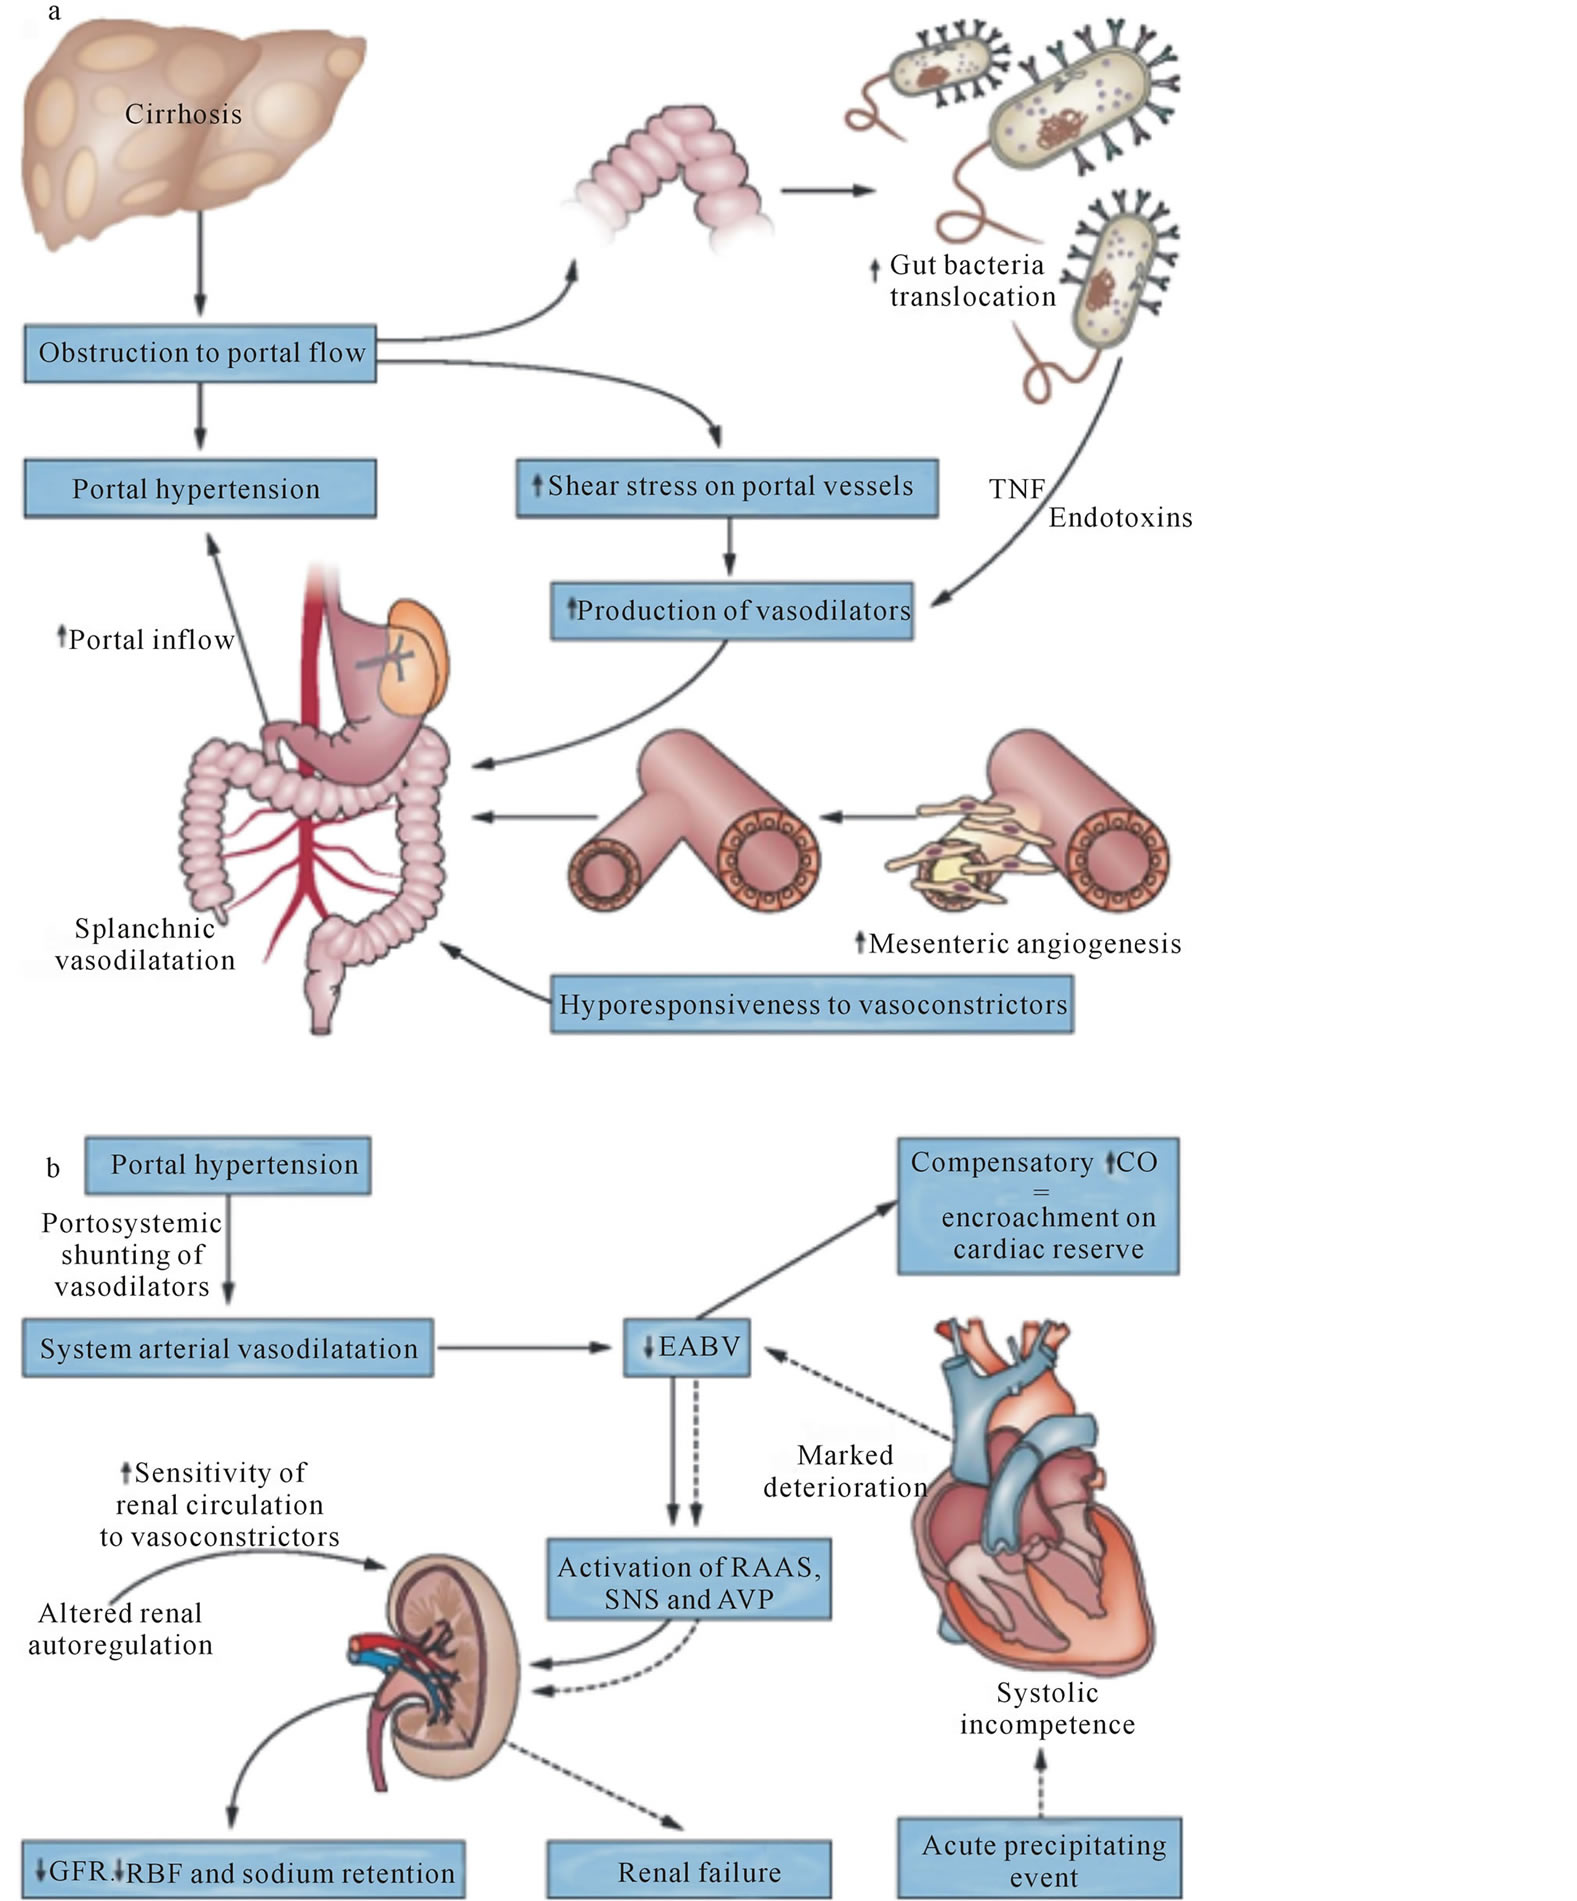
HRS pathophysiology
Pathophysiology of HRS from Scientific research open access

Pathophysiology of HRS

  1. Splanchnic vasodilation
  2. Activation of sympathetic nervous system and renal-angiotensin-aldosterone-system (RAAS)
  3. Cirrhotic cardiomyopathy
  4. Increased vasoactive mediators – LTs, TXA2, endothelins, etc.

Spontaenous bacterial peritonitis (SBP) is the most important risk factor for HRS. 30% patients with SBP may go in HRS.

Prevention of SBP

1. Diuretics: concentrates ascitic fluid raising the opsonic activity of asicitic fluid.

2. Infection treatment: early recognition and treatment of localized infection like cystitis and cellulitis.

3. Restrict proton pump inhibitor: PPI facilitate enteric colonization, overgrowth and translocation into peritoneum.

4. Antibiotic prophylaxis: 1Handbook of Liver Disease By Lawrence S. Friedman, Emmet B. Keeffe

  • Indications:
    1. Cirrhosis with gastrointestinal bleeding
    2. One or more episode of SBP
    3. Ascitic fluid protein <1 gm/dl during hospitalization (US recommendation)
    4. Cirrhosis and ascitic fluid protein <1.5 gm/dl with impaired renal function (creatinine ≥1.2 mg/dl, BUN ≥25 mg/dl or Na+ ≤130 mEq/l) or liver failure (Child pugh score ≥9 and bilirubin ≥3 mg/dl)
  • Choice of antibiotics for prophylaxis:
    • Trimethoprim-sulfamethoxazole (one double strength tabled once daily) OR
    • Ciprofloxacin 500 mg/day OR
    • Norfloxacin 400 mg/day
  • Duration of prophylaxis:
    • For 7 days in patients with cirrhosis and GI bleeding
    • Until hospitalization for patients with ascitic fluid protein <1 gm/dl during hospitalization
    • For other conditions – continue until ascites disappears or decompensated liver disease improves

Management of HRS

  • Terlipressin (vasoconstrictor): 1-2 mg IV every 4-6 hours
  • Albumin: 1 gm/kg (to 100 mg) on day 1 then 20-40 mg daily
  • TIPPS: if response is suboptimal
  • Liver transplant: Optimal

Reference: EASL Clinical Practice Guidelines
127 shares
  • Facebook80
  • Twitter
PGMEE, MRCS, USMLE, MBBS, MD/MS AnesthesiaGastrointestinal systemInternal medicine

Post navigation

Previous post
Next post

Related Posts

PGMEE, MRCS, USMLE, MBBS, MD/MS pth magnesium

Why mild hypomagnesemia causes hyperparathyroidism and severe hypomagnesemia causes hypoparathyroidism?

Feb 16, 2017Jul 29, 2023

You must have seen the statement in First Aid that says – low serum magnesium causes increase in Parathyroid hormone secretion and very low serum magnesium causes decrease in Parathyroid hormone secretion. Doesn’t this make you curious? Let’s explore the underlying mechanism in depth. How Calcium and Magnesium Mediated PTH…

Read More
PGMEE, MRCS, USMLE, MBBS, MD/MS heart sounds area

Heart Sounds – Clinically Explained

Oct 19, 2017Jun 12, 2020

Auscultation (to listen), a clinical procedure done on a daily basis as an aid in diagnosing many disorders, dates back centuries since the Egyptians.  It was then an unaided auscultation (i.e. directly applying the ear to the body).  In 1800’s Dr. Rene Laennec introduced the “Stethoscope” (Chest Scope), rolled paper…

Read More
PGMEE, MRCS, USMLE, MBBS, MD/MS opioid receptors

Opioid Adverse Effects – Mnemonic

Apr 14, 2021Apr 14, 2021

Mnemonic: MORPHINES 1. Miosis Mechanism: Stimulation of Edinger-Westphal nucleus of Cranial nerve III 2. Orthostatic hypotension Mechanism: Vasodilation due to – Direct action decreasing tone of blood vessels Histamine release Depression of vasomotor center 3. Respiratory depression Mechanism: Inhibits respiratory center in a dose-dependent manner (neurogenic, hypercapneic and hypoxic drives…

Read More

Leave a Reply Cancel reply

Your email address will not be published. Required fields are marked *

This site uses Akismet to reduce spam. Learn how your comment data is processed.

Epomedicine. Hepatorenal syndrome (HRS) – Quick revision [Internet]. Epomedicine; 2017 Apr 18 [cited 2026 Nov 7]. Available from: https://epomedicine.com/medical-students/hepatorenal-syndrome-hrs-quick-revision/.

Pre-clinical (Basic Sciences)

Anatomy

Biochemistry

Community medicine (PSM)

Embryology

Microbiology

Pathology

Pharmacology

Physiology

Clinical Sciences

Anesthesia

Dermatology

Emergency medicine

Forensic

Internal medicine

Gynecology & Obstetrics

Oncology

Ophthalmology

Orthopedics

Otorhinolaryngology (ENT)

Pediatrics

Psychiatry

Radiology

Surgery

RSS feed: Ask Epomedicine Ask Epomedicine

  • What to study for Clinical examination in Orthopedics?
  • What is the mechanism of AVNRT?

Epomedicine weekly

  • About Epomedicine
  • Contact Us
  • Author Guidelines
  • Submit Article
  • Editorial Board
  • USMLE
  • MRCS
  • Thesis
©2026 Epomedicine | WordPress Theme by SuperbThemes